The Digital Pathology Illusion: Why Are We Building Storage Instead of Solutions?
Transformation and data harmonization

Digital pathology has finally moved from “nice-to-have” to a global strategic priority. The benefits are real and include remote sign-out, operational efficiency, collaboration, education, and the promise of AI. But as health systems rush to digitize, many are falling for a dangerous misconception: that digital slides automatically equal a valuable dataset.

They don’t.

Right now, we’re witnessing a massive and expensive race to digitize pathology, yet we’re often solving the wrong problem. If your organization’s primary focus is “where to store the pixels,” you’re not building a future for AI, on the contrary, you’re building a more expensive filing cabinet.

The truth: no one wants your slides

It’s time for a reality check: no researcher, pharma partner, or AI developer is looking for “just digital slides.” A WSI in isolation is a clinical dead end and actually a financial liability. Every day that pixel data sits in a silo without clinical context, it consumes storage costs while generating zero insights. A slide only becomes valuable when it’s connected to the patient’s clinical truth and metadata that link to tumor type and subtype, molecular and prognostic markers, treatment course, and outcomes (response, recurrence/progression, survival). Without that context, a WSI is often just a beautiful high-resolution image file with limited real-world utility.

We digitized the workflow, not the intelligence.

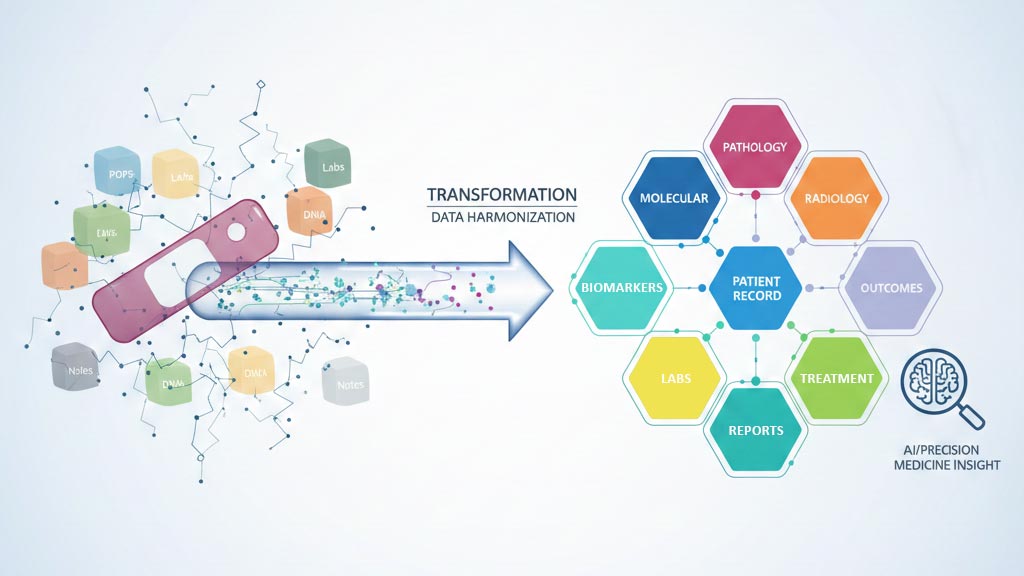
Most institutions today have a “digital pathology” environment that is still a graveyard of silos: slides live in scanner storage or cloud buckets, reports sit elsewhere in the LIS/EMR as static PDFs, and molecular results, labs, treatments, and outcomes remain buried in separate systems or unstructured clinical notes. Even within pathology, the report is still largely narrative text, so downstream “metadata” often stops at age, sex, and diagnosis, while key details like biomarkers, margins, tumor size, staging, and prognostic factors remain trapped in free text. In short: we’ve digitized pathology, but we haven’t structured it, and without structure, we don’t have a dataset, we have digital clutter.

The real dataset is a unified patient story

Real value of the kind that accelerates research, supports precision medicine, and enables reliable AI only exists when data is multi-modal, longitudinal, and semantically organized. That means slides are programmatically linked to pathology findings, biomarkers/molecular data, labs, radiology, treatment events, and outcomes, following the patient journey over time. Researchers don’t search for “tumor” vs “cancer” vs “malignancy”. They search by clinical meaning: triple-negative breast cancer, EGFR-mutated lung adenocarcinoma on targeted therapy, high-risk disease with recurrence. That requires semantic organization, not just storage.

And this is becoming urgent. We’re entering the era of tabular foundation models, where AI learns from structured clinical tables at scale. These models are only as good as the structure and consistency of the data they ingest. Messy, disconnected silos don’t just slow AI down, they undermine its reliability.

The bottom line

“The goldmine of pathology data” will remain a hollow promise until we stop treating the image as the final product. The image is the starting line. The dataset is the unified, searchable, longitudinal record of the patient’s life.

Stop asking: “Where do we store the slides?” Start asking: “How do we build a structured data foundation that connects the pixels to the patient, automatically and at scale?”

If you aren’t solving for data structure, you aren’t solving the problem.

Pathologists are not just the users of these systems; they are the architects of the clinical truth. If the pathologist doesn’t define the structure at the point of capture, the data is lost to the “narrative abyss” of a PDF forever. But realizing its full translational value requires partnership with strong technical teams who understand structured data design, concept libraries and standardized ontologies, flexible database architectures, tabular foundation models, and semantic search. Together, we can turn stored pixels into the most valuable data in healthcare that powers trustworthy AI and ensures every patient receives the right treatment at the right time.

About the Author

Dr. Rajendra Singh is a Professor of Pathology at the University of Pennsylvania and co-founder of PathPresenter. He serves as a member of the Digital and Computational Pathology Committee of the CAP, Editorial Board of the WHO for Classification of tumors, 5th Edition and the Board of Digital Pathology Association.

Success Story: Accelerating Clinical Trials for Oncology with Imagenomix Predict and PathPresenter ConsultConnect

Zero-footprint web portals and AI-enhanced workflows reduce screening bottlenecks for an AKT-Pathway clinical trial

Laboratory scientists

In Brief

  • Oncology research trials require patients but enrollment can be a major limiter. 40% of oncology trials fail due to under-enrollment and 80% do not meet enrollment timelines
  • Imagenomix addresses the enrollment challenge: Imagenomix’s Predict AI model for rapid mutation prediction from H&E slides speeds patient enrollment in clinical trials and lowers trial costs
  • To recruit enough patients, clinical trials often include dozens of trial sites. This creates new challenges in collecting and aggregating data for analysis and reporting when those sites do not share the same laboratory and IT systems
  • PathPresenter ConsultConnect solves the interoperability challenge by accepting and aggregating data from all trial sites into one data store, allowing efficient, concentrated and centralized analysis and reporting. Being cloud based, vendor-agnostic and built for interoperability, ConsultConnect requires no shared IT infrastructure or local software installation, and it accepts images from virtually any whole slide scanner or format.

The Challenge of Patient Enrollment

Clinical trials are the lifeblood of oncology research, providing the evidence that transforms promising therapies into approved treatments. Yet, patient enrollment remains one of the most persistent obstacles to trial success. Studies show that 40% of oncology trials fail due to under-enrollment, and 80% fail to meet enrollment timelines. The consequences are significant: delays in bringing lifesaving therapies to patients, higher trial costs, and incomplete or inconclusive data.

A key reason for insufficient enrollment lies in the complexity of matching the right patients to the right trial in timely fashion. Molecularly driven oncology trials depend on identifying specific genetic mutations, gene fusions, or molecular signatures in a patient’s tumor. These molecular biomarkers determine eligibility and help researchers understand which patients are most likely to benefit from an investigational therapy. Unfortunately, traditional laboratory workflows are slow, labor-intensive and expensive. Next-generation sequencing (NGS), while accurate, typically takes three to four weeks to deliver results and requires substantial tissue samples. The cost and delay not only slow patient enrollment but may also disqualify patients whose clinical status changes before testing is complete.

Accelerating Enrollment with AI

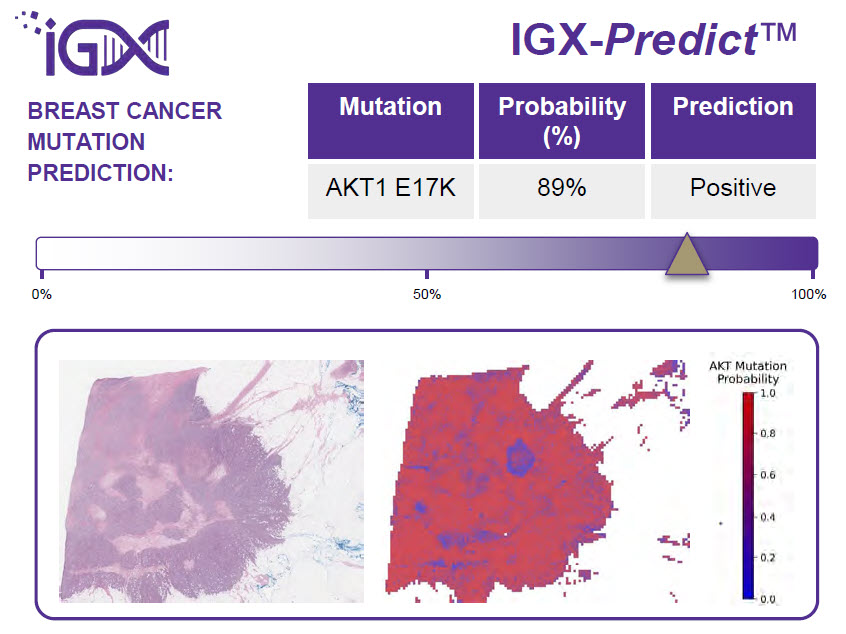
Imagenomix set out to solve this enrollment challenge by developing a faster, more scalable approach to patient screening through digital pathology and AI predictive models. Its IGX Predict AI-based technology analyzes the H&E-stained biopsy whole slide images that are already part of digital pathology workflows to predict the presence of key genetic mutations. Using advanced deep-learning models, IGX Predict identifies subtle histologic patterns correlated with genomic alterations, returning results in minutes instead of weeks. Predicted mutations are then confirmed by a multi-gene panel or a low-cost single gene assay, enabling clinical trial screening and enrollment even in low-income settings, for patients who do not have access to large NGS panels.

IGX Predict

IGX Predict AI mutational screening enables clinicians and researchers to assess far more patients, more quickly, and at lower cost. Instead of waiting weeks for sequencing results, trial coordinators can rapidly identify patients who are likely to qualify for a given study and prioritize them for confirmatory testing or immediate enrollment. The result is faster trial startup, reduced screening costs, and greater access for patients who may benefit from investigational therapies.

By using AI to triage patients and predict mutation profiles, Imagenomix helps sponsors overcome one of the most critical barriers in oncology research: finding enough qualified participants to power statistically meaningful trials in a timely fashion.

From Enrollment Success to Data Management Complexity

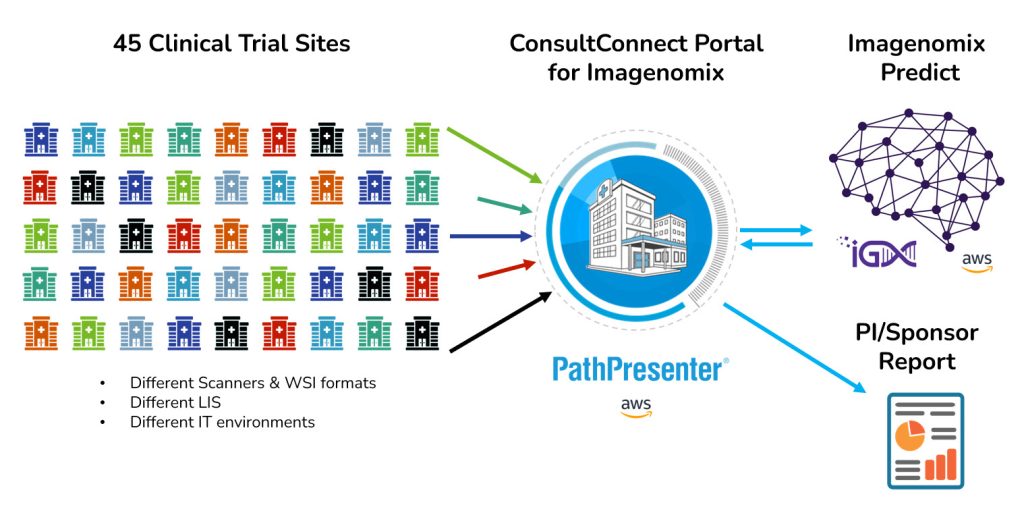
In a current multi-site oncology study, the Imagenomix approach is enabling rapid enrollment across 45 clinical trial centers. With the enrollment hurdle cleared, a new challenge emerges: how to manage and harmonize the flood of data generated by dozens of institutions operating with different laboratory and IT infrastructures.

Each center has its own scanners, laboratory information systems (LIS), and compliance requirements. Some hospitals prohibit local software installation, making it difficult to deploy analysis tools or data transfer agents. Trial sponsors and investigators need a single, secure system to collect, store, and analyze digital pathology data from every site, regardless of scanner type, file format, or local IT policy.

Consistent, centralized access is also essential for quality control and reporting. Pharmaceutical sponsors require unified access to trial results and the ability to review data from all sites without the delays caused by manual data consolidation.

The Solution: PathPresenter ConsultConnect

To address these challenges, Imagenomix partnered with PathPresenter, integrating its ConsultConnect platform as the data backbone of the trial. Designed for multi-site, multi-platform interoperability, ConsultConnect is a cloud-based, vendor-agnostic solution that accepts images from virtually any whole-slide scanner or file format. It requires no local installation or shared IT infrastructure, making it ideal for diverse hospital environments with strict security policies.

Within days, PathPresenter deployed a secure ConsultConnect web portal on AWS specifically for the Imagenomix Predict platform. Using this platform, each pathology laboratory and trial site can safely upload data directly to the portal without any software installation, slide image adjustments or configuration burden. Each site sees only their respective cases while participating in a large multicenter study. The platform’s intuitive web interface built for pathologist by pathologists requires minimal training and facilitates rapid adoption across geographically distributed teams. Each site and each submitting pathologist has unique login credentials, providing traceability and ensuring no data leakage between sites.

ConsultConnect Portal for Imagenomix clinical trial

Once uploaded, the data is automatically organized into a centralized repository. Imagenomix’s IGX Predict AI algorithms operate in the cloud to analyze the slides and generate mutation predictions. Results are seamlessly delivered back through the ConsultConnect portal, where they can be accessed by trial investigators and sponsors.

ConsultConnect’s robust healthcare-grade security and privacy controls ensure compliance with patient data protection regulations, while its scalable cloud architecture supports efficient, high-volume processing of digital slides.

Results and Impact

The combination of Imagenomix Predict and PathPresenter ConsultConnect is transforming the operational efficiency of the trial.

  • Faster Trial Execution: With IGX Predict’s AI-based mutation prediction, patient identification that once took weeks now takes minutes, accelerating recruitment and trial initiation.
  • Simplified Data Management: ConsultConnect eliminates the need for complex software deployments and manual data aggregation. All centers are able to contribute data seamlessly to a unified cloud environment.
  • Enhanced Collaboration: Investigators and sponsors gain centralized visibility into results, supporting real-time collaboration and decision-making across sites.
  • Improved Cost and Efficiency: Reduced reliance on costly molecular testing and streamlined data workflows translates into substantial savings in time, tissue and cost.
  • Scalable Model for Future Trials: The success of this implementation establishes a repeatable, scalable model for future oncology and biomarker-driven studies involving multi-site data collection.

A Blueprint for the Future of Oncology Research

This case study illustrates how combining AI-driven mutation prediction with cloud-based interoperability can redefine the pace and efficiency of clinical research. Imagenomix Predict tackles the most pressing barrier of patient enrollment, while PathPresenter ConsultConnect resolves the data-logistics challenge inherent in large, distributed trials.

Together, they enable sponsors to run faster, more cost-effective studies without compromising scientific rigor or patient privacy. As oncology trials continue to grow in complexity and precision, such integrated, interoperable technologies will be indispensable in bringing the next generation of targeted therapies to patients worldwide.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.

Why Seamless IMS-LIS Integration Is Essential for Digital Pathology

Unified digital workflows connecting IMS to LIS unlock efficiency, compliance, and the full potential of AI for modern pathology

Digital pathology has moved decisively from experimentation into everyday practice. For pathology organizations, it now underpins clinical workflows, operational efficiency, and long-term strategy. To enable remote sign-out and AI-driven analysis, organizations have turned to Image Management Systems (IMS) that can organize, track, and contextualize whole slide images across the diagnostic workflow.

However, the data needed to interpret those images extends well beyond what an IMS typically manages. Patient demographics, clinical context, specimen metadata, test orders, results, finalized reports and more all live in a separate but equally critical system: the Laboratory Information System (LIS). For groups accustomed to thinking primarily in terms of image workflows, the LIS can feel like a parallel universe, yet it is the system of record for nearly all non-image pathology data. When IMS and LIS platforms operate in isolation, inefficiencies emerge, context is lost, and the promise of digital pathology remains only partially realized.

As digital pathology programs mature, it is becoming evident that success depends not only on performance, scale, and regulatory readiness, but also on seamless interoperability. In this article, we explore why deep, context-aware integration between an IMS and a modern LIS is essential to unlocking the full value of digital pathology. We’ll examine the practical challenges this integration resolves and the strategic benefits it enables for pathology groups advancing toward a fully digital, AI-enabled future.

Image Management Systems (IMS) in Digital Pathology

A digital pathology image management system (IMS) goes far beyond mere image viewing. At its best, it is an enterprise-grade platform designed to manage the entire lifecycle of digital pathology images across clinical, research, and educational workflows, and serving as the backbone of digital pathology operations, supporting everything from secure storage to AI integration and multi-institution collaboration.

Core Capabilities of a Modern Digital Pathology IMS

A robust IMS typically includes:

  • Advanced Slide Viewing: High-performance visualization across multiple formats (SVS, NDPI, SCN, DICOM, BigTIFF, and more), synchronized multi-slide viewing, annotations, overlays, and fast rendering.
  • Centralized Data Management: Secure, scalable image storage, on-premises, cloud, or hybrid, with governance controls and long-term data stewardship.
  • Security and Compliance: HIPAA-grade protections, encryption, audit trails, role-based access, and regulatory readiness for clinical use.
  • Workflow Integration: Case management, task tracking, and seamless interoperability with LIS, EHR, PACS, and other enterprise laboratory software systems.
  • User Roles and Access Control: Granular permissions ensure that only authorized users access sensitive data, while maintaining accountability.
  • Collaboration Tools: Support for remote consults, tumor boards, education, and peer review through shared environments.
  • AI and Image Analysis Enablement: Integration with AI models for detection, quantification, and pattern recognition, embedded directly into diagnostic workflows.
  • Regulatory Readiness: Many IMS platforms are designed to meet FDA, HIPAA, GDPR, IVDR, and other regulatory standards. Some, such as PathPresenter’s clinical viewer, are FDA 510(k) cleared and EU-IVDR certified for primary diagnosis when paired with approved scanners.

In short, an IMS provides a comprehensive infrastructure for digital pathology. It can be highly capable on its own, handling slide storage, visualization, annotations, and even AI outputs. But when it operates independently from the laboratory’s core operational system, its impact is inherently limited. Rather than dissolving legacy barriers, a disconnected IMS can unintentionally recreate them in digital form.

True digital pathology maturity is reached only when images and laboratory data function as a single, coherent workflow. Without that alignment, pathology groups often find themselves managing parallel systems that never quite converge.

The Operational Cost of Keeping IMS and LIS Separate

When image workflows and laboratory workflows are not connected at a foundational level, pathology teams encounter familiar but amplified challenges, including:

  • Reliance on manual reconciliation of cases and slides
  • Repeated entry of patient and specimen data
  • Frequent toggling between systems during case review
  • Greater exposure to mismatches, omissions, and reporting errors
  • Disjointed compliance records spanning multiple platforms
  • Collaboration slowdowns across sites and subspecialties

In isolation, each issue may seem manageable. At scale however, particularly in regulated, high-throughput environments, they compound rapidly, eroding both efficiency and confidence in the digital workflow.

Rethinking the LIS: More Than a Back-End Database

For many digital pathology teams, the LIS is perceived primarily as a static repository: the place where orders originate and reports ultimately land. While that historical role remains essential, it no longer reflects how modern laboratories operate.

From Passive Record-Keeping to Active Workflow Orchestration

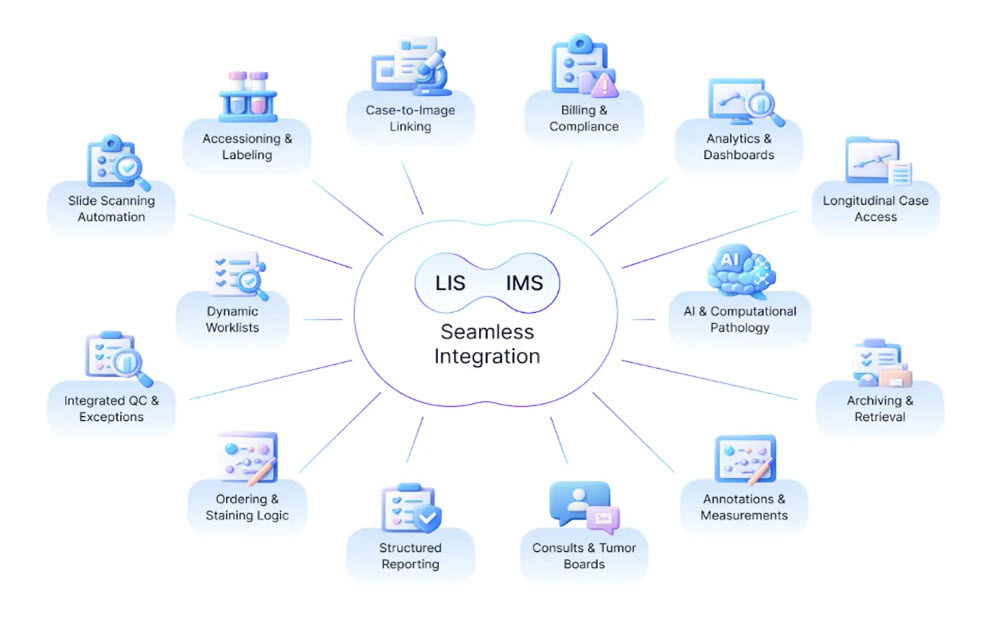
Today’s laboratories increasingly require systems that do more than store information. A modern LIS such as LigoLab functions as an operational engine: driving workflow logic, enforcing rules, automating handoffs, and presenting the right context at the right moment.

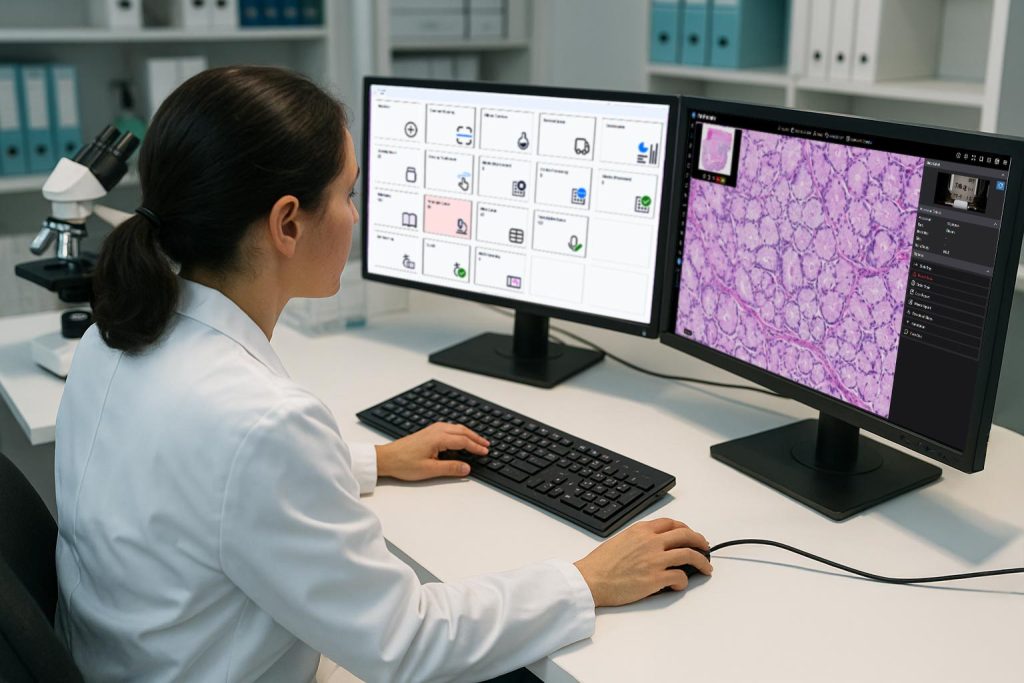
When an IMS is natively integrated into this environment, digital pathology is no longer an external tool that users “visit.” Instead, image review becomes a natural extension of the laboratory workflow, governed by the same logic, permissions, and traceability as the rest of the case lifecycle.

What Integrated LIS–IMS Workflows Enable Day to Day

In a genuinely unified digital pathology environment:

  • Digital slides are opened directly from the laboratory case, not searched for separately
  • Patient, specimen, and order context flows automatically into image review
  • Movement between data, images, and reports feels continuous rather than segmented
  • Auditability covers both diagnostic decisions and image interactions end to end
  • AI outputs appear within established workflows rather than as side-channel tools

This level of integration changes how work is performed: not by adding features, but by removing friction.

LIS-IMS integration

Core Challenges Solved by Deep Integration

1. Smoother, Faster Diagnostic Workflows

When image access is embedded within the laboratory system, pathologists spend less time navigating software and more time interpreting cases. Reduced friction translates directly into faster turnaround and lower cognitive load.

2. Scalable Support for Remote Practice

Integrated platforms make location largely irrelevant. Secure remote sign-out, real-time collaboration, and distributed subspecialty review become standard operations rather than exceptions.

3. Better Decisions Through Complete Context

Images rarely tell the full story on their own. Tight coupling between LIS and IMS ensures that diagnostic interpretation always occurs alongside the complete clinical and specimen context, reducing the risk of incomplete assessment.

4. Stronger Governance and Compliance

When images and laboratory data share a unified audit framework, compliance with regulatory and accreditation requirements becomes simpler and more defensible—without added administrative burden.

5. A Practical Path to Enterprise AI

AI delivers value only when it operates inside real workflows. Integrated LIS–IMS environments provide the governance, data access, and workflow hooks required to deploy AI responsibly and at scale.

Integration in the Real World: From Concept to Practice

A practical example of this approach can be seen in the collaboration between PathPresenter and LigoLab. Rather than treating image management as an external system, PathPresenter’s clinical viewer is embedded directly within LigoLab’s enterprise laboratory platform.

The result is a unified diagnostic experience where pathologists interact with slides in the same environment where cases are managed, orders are tracked, and reports are finalized. This tight coupling reduces navigation overhead, accelerates review cycles, and establishes a solid foundation for future AI-driven enhancements.

Related: LigoLab and PathPresenter Announce Strategic Partnership to Deliver Seamless Digital Pathology Workflows

Building Toward a Unified Digital Pathology Future

At its core, LIS–IMS integration is not about software convenience. It is about redefining how pathology work flows from accessioning through diagnosis and reporting.

When laboratory data and images operate as one system:

  • Operations gain visibility and automation
  • Financial teams benefit from cleaner alignment with billing and revenue workflows
  • Clinical staff gain modern tools that reduce manual effort
  • Patients benefit from faster, more consistent diagnostic outcomes

As digital pathology, AI, and remote diagnostics continue to evolve, this alignment moves from “nice to have” to mission critical. Pathology groups that invest early in deep, contextual integration position themselves not just to digitize slides, but to fundamentally modernize how pathology is practiced.

More Information

Looking for a new (or improved) LIS-IMS integration? Connect with our team to assess your workflow needs and explore the best solution.

Digital Pathology Basics: Image Viewers vs. Image Management Systems

Image Viewer vs IMS comparison

In brief

  • An image viewer focuses on the basics of viewing and interacting with digital slides.
  • A digital pathology IMS manages the entire lifecycle of digital pathology images within a clinical, research, or educational workflow.

As digital pathology becomes more integrated into clinical, academic, and research settings, it’s important to distinguish between the tools used in this domain. Two common types of software encountered are pathology slide viewers and digital pathology image management systems (IMS). While they may appear similar on the surface (both enable users to access and interact with digital slides) they are fundamentally different in terms of scope, features, and intended use.

Pathology Slide Viewer: A Focused Viewing Tool

A pathology slide viewer is a software application designed primarily for visualizing digitized pathology slides, also known as whole slide images (WSIs). These tools typically allow users to open and navigate high-resolution scans of tissue specimens. Common features include zooming, panning, rotation, and the ability to add simple annotations or measurements.

These viewers can be used by pathologists for reviewing cases, by students for learning, or by researchers for image analysis. They may be standalone desktop applications or web-based platforms. Some viewers are vendor-specific, tied to a particular scanner or image format, while others are open source or multi-format compatible. However, pathology slide viewers are limited in scope. Their main purpose is to enable manual, visual inspection of slides. They typically do not provide broader workflow functionality, user management, or system integrations. For small-scale or individual use, slide viewers are handy tools. But their limitations will quickly become apparent.

Digital Pathology Image Management System (IMS): A Comprehensive Platform

In contrast, a digital pathology image management system (IMS) such as PathPresenter is a comprehensive, enterprise-grade software solution that manages the entire lifecycle of digital pathology data. It includes not only the viewing of whole slide images, but also the organization, tracking, analysis, and sharing of those images in clinical and research workflows. An enterprise deployment of an integrated digital pathology workflow will almost certainly require a fully featured IMS.

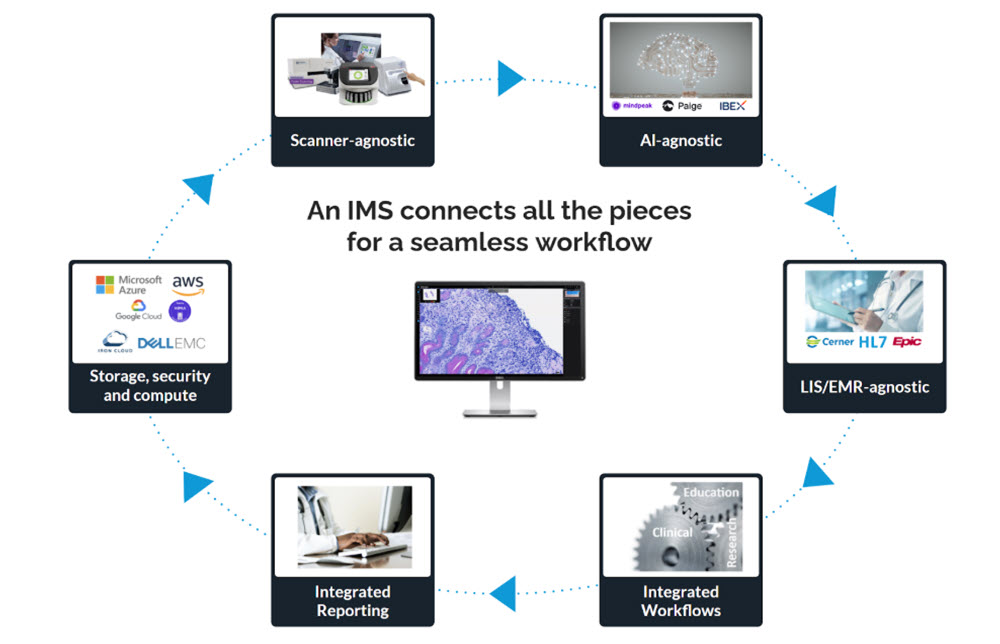
IMS connects all the pieces for a seamless workflow

A robust IMS typically includes the following core capabilities:

  • Slide Viewing: IMS platforms provide high-quality visualization with features like synchronized multi-slide viewing, annotation, overlays, and fast rendering across many file formats (svs, ndpi, scn, dcm, bigtiff, etc.).
  • Data Management: IMS centralizes and secures pathology data with on-premise, cloud, or hybrid storage options.
  • Security: IMS must meet strict standards (e.g., HIPAA), ensuring PHI confidentiality, integrity, and availability while protecting against threats.
  • Workflow Integration: Platforms support case management, task tracking, and diagnostic, research, or education workflows, often with integrated security like SSO.
  • User Roles & Access Control: Permission-based access and audit trails ensure only authorized users can view sensitive data while maintaining accountability.
  • Interoperability: IMS integrates with LIS, PACS, EHR, and other systems. PathPresenter is vendor-agnostic, with integrations to leading systems such as EPIC Beaker and LigoLab.
  • Collaboration Tools: Multi-user environments enable real-time sharing, remote consults (e.g., PathPresenter’s ConsultConnect), and team-based diagnosis or education.
  • AI and Image Analysis: Advanced IMS platforms integrate AI for detection, quantification, and pattern recognition. PathPresenter partners with leading vendors including Paige, Aisencia, Aiforia, MindPeak, Pictor Labs, Primaa, DeepLIIF, DiaDeep, Artera and IBEX to embed models within its workflow. PathPresenter powers the College of American Pathologists’ (CAP) AI Studio, which lets member test drive AI models from multiple vendors in one site with a common UI.
  • Regulatory Compliance: IMS solutions are generally designed to meet HIPAA, FDA, GDPR, and or IVDR standards depending on the application and jurisdiction. PathPresenter’s clinical viewer is FDA 510(k) cleared and EU-IVDR certified for primary diagnosis with approved scanners.

Key Differences and Use Cases

While both a slide viewer and an IMS allow for digital slide visualization, their purposes differ greatly. A slide viewer is ideal for simple, low-volume, or individual use cases, such as academic review, research projects without extensive collaboration, or basic diagnostic reference. It is generally easy to deploy and use, and may come free of charge or at a low cost.

A digital pathology IMS, on the other hand, is suitable for high-volume, regulated environments such as hospitals, diagnostic labs, and collaborative research institutions. These systems are designed to scale with demand, handle multi-user scenarios, and provide robust governance and compliance. They also support complex workflows involving multiple roles, locations, and datasets.

Choosing between a viewer and an IMS depends on the specific requirements of the organization or individual, whether it’s ease of access and simplicity, or full integration, scalability, and workflow optimization.

More Information

Not sure if a viewer or IMS is right for you? Connect with our team to assess your workflow needs and explore the best solution.

Choosing the Right Digital Pathology Workflow Partner: So Many Options

Digital pathology is rapidly evolving into a central component of modern diagnostics, education, and research. The adoption of whole slide imaging, artificial intelligence (AI), and cloud-based platforms is reshaping workflows and collaboration. But technology alone does not guarantee success—choosing the right workflow partner is the critical factor that determines whether digital transformation delivers meaningful impact.

Core Elements of a Strong Workflow Partnership

1. Domain Knowledge and Expertise of the Vendor

Every digital pathology journey is a journey, so choosing a vendor with deep domain knowledge and expertise is critical. To consider:

  • Does the vendor have extensive experience in pathology workflows?
  • Are they able to identify the gaps in pathology workflows?
  • Do they have the experience to serve as a guide to a successful implementation?

Domain expertise and experience contribute directly to a successful implementation.

2. Interoperability

A digital pathology platform must integrate seamlessly with existing systems. This includes:

  • LIS/EMR compatibility through HL7, DICOM, and other standards.
  • Support for diverse file formats (WSI, JPEG, DICOM).
  • Ability to integrate scanners, AI tools, and storage infrastructure.

Interoperability ensures that digital pathology becomes part of the clinical workflow, not an isolated add-on.

3. Scalability and Flexibility

Institutions vary in size and needs, but a platform should be able to grow with them. Key factors include:

  • Handling both small-scale implementations and large archives of millions of slides.
  • Flexible deployment models (cloud, hybrid, on-premise).
  • Configurable workflows that adapt to clinical, educational, and research use cases.

A scalable partner protects investments and avoids costly migrations later.

4. Security and Compliance

Patient data and digital slides are sensitive assets. A trusted partner must provide:

  • HIPAA-compliant infrastructure.
  • Strong data encryption and access controls.
  • Transparent chain-of-custody management.
  • Regular security audits and compliance certifications.

This foundation ensures safety, trust, and regulatory alignment.

5. User Experience and Adoption

Even the most advanced technology fails if users resist it. A partner should prioritize:

  • Intuitive user interfaces that mimic the glass slide experience.
  • Tools that support pathologists’ natural workflows (annotation, conferencing, consults).
  • Minimal technical barriers for both in-house and remote users.

Familiarity breeds confidence, leading to higher adoption and satisfaction.

6. AI Enablement and Future-Proofing

Digital pathology is closely tied to AI innovation. An ideal partner should:

  • Support annotation tools for AI training and validation.
  • Offer seamless deployment of algorithms within the workflow.
  • Provide APIs and middleware for integration with multiple vendors.

Future-proofing with AI ensures the platform remains relevant as the field advances.

7. ROI and Value Creation

Institutions must justify investment with clear returns. Value comes from:

  • Reduced storage and logistics costs.
  • Faster turnaround times for consultations and sign-outs.
  • Enhanced collaboration and education opportunities.
  • Ability to monetize research data through partnerships.

The right partner helps institutions build a compelling business case.

8. Collaboration and Cultural Fit

Technology is only half of the equation; the other half is people. The partner should demonstrate:

  • Willingness to co-develop solutions.
  • Strong track record of customer engagement and support.
  • Transparent communication and long-term commitment.

A true partner invests in mutual success rather than a transactional relationship.

Future Directions

Digital pathology partnerships will increasingly be shaped by:

  • Standardization through DICOM adoption and interoperability frameworks.
  • Enterprise imaging integration, aligning pathology with radiology and other disciplines.
  • Practical AI applications, moving from hype to validated, clinically useful tools.

These trends will demand partners who are both innovative and realistic, balancing future readiness with present-day reliability.

Conclusion

Choosing the right digital pathology workflow partner is about creating bridges—between systems, between people, and between present workflows and future possibilities. The decision should be guided by interoperability, scalability, security, usability, AI readiness, ROI, and cultural fit.

When these elements align, institutions unlock the full potential of digital pathology: efficient operations, powerful collaboration, enriched education, and most importantly, improved patient care.

More Information

PathPresenter has guided a wide range of organizations to success on their digital pathology journey. Interested in discussing your own challenges? Contact us.

Pathoverse Part 6: DeepLIIF Virtual Restaining for Scalable, High-Accuracy Pathology AI

This article summarizes part 6 of our “Into the Pathoverse” webinar, recorded at Pathology Visions 2025 in San Diego and available on-demand. This segment starts at 43:00 in the full video. Watch the full video.

In one of the most technically exciting segments of the Pathoverse webinar, Dr. Saad Nadeem of Memorial Sloan Kettering Cancer Center (MSK) described how a research project called DeepLIIF has evolved into one of the first AI platforms deployed clinically across both pathology and surgery within a research lab. DeepLIIF, a virtual (re)staining and quantification framework, is poised to transform biomarker interpretation by improving consistency, segmentation accuracy, and dynamic range across a broad set of diagnostic markers.

Dr. Nadeem’s team has spent four years building and validating DeepLIIF, driven by a fundamental problem in pathology: extreme inter-observer variability for certain cell types and biomarkers. When macrophage interpretation can vary by as much as 80% between experienced pathologists, traditional annotation and any AI model trained on those annotations faces major limitations. DeepLIIF was designed to overcome that barrier by anchoring its predictions in perfectly co-registered biology.

A New Approach to Virtual Staining

DeepLIIF relies on a unique dataset architecture. On a single tissue section, Dr. Nadeem’s group performs multiplex immunofluorescence (mIF) staining, generating high-resolution ground truth for markers such as magenta for tumor cells, green for macrophages, and red for lymphocytes.

The same tissue is then re-stained with IHC and H&E. Because these images are perfectly co-registered down to the subcellular level, DeepLIIF’s machine learning models learn direct pixel-to-pixel transformations. The result: the ability to take a standard H&E or IHC image and virtually convert it into multiple fluorescent channels and segmentation outputs.

A key advantage lies in the dynamic range of mIF. Traditional DAB-based brightfield IHC has limited range, complicating interpretation for biomarkers like HER2-low or HER2-ultralow. DeepLIIF synthesizes high-dynamic-range equivalents, enabling more sensitive classification.

This work formed the basis of a major publication in Nature Machine Intelligence, where the algorithm demonstrated strong generalizability across markers, modalities, and tissue types.

From Open Source to Clinical Deployment

DeepLIIF launched publicly in January 2022 as a free, open-source tool at DeepLIIF.org, and its adoption has been swift. Today the platform has:

  • 23,000 GitHub downloads
  • 3,500 daily user sessions, a scale that rivals or surpasses many commercial vendors
  • Support for 30+ markers across hematopathology, surgical pathology, and cytopathology
  • Global usage, with ~30% of slides submitted from outside MSK

DeepLIIF remains MSK-patented but they have made it openly accessible, ensuring both scientific transparency and protected clinical rigor. Behind the scenes, the team continues rigorous validations across markers and cancer types. DeepLIIF’s clinical potential is rapidly expanding, with HER2 and PD-L1 support expected within weeks, followed by additional high-impact biomarkers.

DeepLIIF Integrated Into PathPresenter and CAP AI Studio

A pivotal milestone came when DeepLIIF integrated directly into PathPresenter, MSK’s primary image management system and a core pillar of the Pathoverse ecosystem. This integration enables slide ingestion, visualization, AI inference, and reporting in a unified workflow—critical for clinical translation.

Another major advancement is DeepLIIF’s availability in the CAP AI Studio, a platform launched by the College of American Pathologists and powered by PathPresenter. Through the CAP AI Studio, users can test drive a variety of AI models from multiple leading vendors with no cost and no risk. In the case of DeepLIIF, the CAP AI Studio lets CAP members try out 20+ stains on preloaded images, lasso regions of interest (ROIs), and receive quantifications in milliseconds.

Dr. Nadeem emphasized that even datasets as large as 5 million slides can be processed in real time using the system’s optimized AI–human collaboration model. This sets the stage for large-scale biomarker analysis across institutions.

Path to FDA Adoption

DeepLIIF’s clinical implementation has already begun. Working with Dr. Matt Hanna and MSK’s pathology leadership, the team secured New York State Laboratory Developed Test (LDT) approval for KI67/ER/PR in breast cancer. Next steps include FDA single-site submissions for multiple markers, supported by PathPresenter’s enterprise-grade workflows.

The projected clinical workload is significant:

  • 80,000+ slides annually today
  • 120,000+ slides per year once HER2 and PD-L1 modules launch

AWS plays an important role here as well. Dr. Nadeem noted that the DeepLIIF deployment on AWS is now “as cost-efficient as any commercial vendor,” enabling high-throughput inference at sustainable scale.

Expanding the Marker Ecosystem

DeepLIIF continues to grow its marker library, including PANCK, additional tumor markers, lymphocyte markers, and macrophage markers. These expansions will enable important scoring systems such as CPS (combined positive score), supporting companion diagnostics and immunotherapy workflows. The long-term vision includes converting routine IHC into virtual multiplex immunofluorescence—unlocking insights that typically require costly, specialized platforms.

DP4ALL: Digital Pathology for All

One of the most innovative parts of Dr. Nadeem’s presentation was the introduction of DP4ALL, the “Digital Pathology for All” initiative. This program responds to a frequent request from colleagues in low-resource settings: How can we digitize slides without a scanner? DP4ALL provides exactly that. Using only a basic microscope, a low-cost smartphone adapter, and a navigation-style microscope video.

Users anywhere in the world can upload short videos to the DeepLIIF platform. The system automatically:

  • Stitches video frames into a whole-slide image
  • Supports 10x, 20x, and 40x magnification
  • Allows region-of-interest selection
  • Generates shareable URLs that can be sent instantly via messaging apps

The tool is stain-agnostic, supporting H&E, IHC, and special stains. It has already been validated on more than 1,000 whole-slide reconstructions.

MSK generously supports the program, allowing the team to process 20,000–30,000 slides per year, free of charge. While this tool will never replace high volume commercial scanners in dedicated labs, it does dramatically reduce the barriers to entry into digital pathology, allowing almost any pathologist or institution to start their journey, get their toes wet and begin to prove the value of digital pathology to themselves and others. 

A Global Vision for Accessible AI Pathology

Dr. Nadeem closed by encouraging attendees to explore the platform and provide feedback. His team’s work, spanning open-source tools, clinical deployment, advanced imaging science, and global access initiatives, exemplifies the Pathoverse’s core mission: connecting research, clinical workflows, and technology to improve pathology everywhere.

DeepLIIF’s journey from NYU concept to MSK clinical engine demonstrates how the right combination of AI, cloud infrastructure, and interoperable platforms like PathPresenter can bring next-generation diagnostics into everyday practice at global scale.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.

Pathoverse Part 7: This is Just the Beginning

This article summarizes part 7of our “Into the Pathoverse” webinar, recorded at Pathology Visions 2025 in San Diego and available on-demand. This segment starts at 53:32 in the full video. Watch the full video.

In the closing segment of the Pathoverse webinar, Dr. Raj Singh brought the day’s presentations into powerful focus. Across all the innovations showcased—from remote consult workflows and cloud infrastructure to AI-driven trial acceleration and virtual restaining—one message became unmistakably clear: the future of pathology will be built through collaboration, interoperability, and shared purpose.

Dr. Singh emphasized that the collective work taking place across leading academic centers, technology companies, AI laboratories, and global clinical partners represents only the beginning. The solutions presented throughout the event—ConsultConnect, Grundium’s scanners, AWS HealthImaging, Imagenomix Predict, DeepLIIF, and more—are not isolated projects. They are foundational components of a much larger transformation.

Pathology at the Center of Precision Medicine

Raj began by reflecting on the extraordinary talent contributing to this transformation. The partners represented during the webinar come from world-class institutions and companies, each pushing the boundaries of what digital pathology can accomplish. Together, he argued, they are redefining the role of pathology within precision medicine.

Historically, pathology has often been perceived as a diagnostic endpoint: a final confirmation at the end of a process. But the industry is changing. With high-resolution whole-slide imaging, AI-augmented interpretation, cloud-enabled data exchange, and global-scale collaboration, pathology is rapidly becoming a central engine for precision healthcare.

Digital pathology is now informing clinical trials, helping select targeted therapies, powering biomarker discovery, supporting global consultations, and enabling real-time quantitative analysis at speeds unreachable in the analog era. The field is no longer asking why digital pathology is needed—it is asking how far and how fast it can go.

Digital Pathology as a Growth Engine—not a Cost Center

Dr. Singh highlighted a mental shift underway at top institutions such as MSKCC, OSU, UPMC, and Mayo Clinic. These organizations have moved beyond the early questions of implementation, cost, or justification. Today, they see digital pathology as a strategic growth driver, a way to expand service lines, accelerate research, support global collaborations, and unlock new revenue streams.

The traditional framing of digital pathology as an expensive technology investment is fading. In its place is a new understanding: when integrated into a platform like PathPresenter, digital pathology becomes a source of clinical efficiency, innovation, and institutional differentiation.

Through examples shared earlier in the webinar, Raj illustrated how labs are already extracting value:

  • Consultation as a service, enabled by ConsultConnect
  • AI as a service, allowing institutions to run third-party models on demand
  • Research and industry partnerships, powered by large-scale, interoperable datasets
  • Accelerated clinical trials, through platforms like Imagenomix Predict
  • Workflow efficiencies, through integrated viewers, cloud infrastructure, and AI-driven insights

When institutions collaborate and leverage shared digital infrastructure, the economics of pathology change and the benefits multiply.

Unlocking the Value of Data Through Collaboration

A major theme of Dr. Singh’s conclusion was the growing ability of institutions to unlock the value of their data. Through PathPresenter, hospitals can share de-identified data securely with partners, run AI modules from a variety of vendors, or even support other institutions by offering AI inference as a service.

This model expands access in meaningful ways. A lab that uses a specific algorithm only a handful of times per year no longer needs long-term contracts or licenses; instead, they can upload a slide to a participating institution’s portal and receive results immediately. This approach mirrors the transformation seen earlier with digital consults, and represents the next phase of democratized AI in pathology.

A Global Network of Connected Hospitals

Dr. Singh emphasized that PathPresenter’s vision is profoundly global. While the platform already supports the largest network of U.S. institutions using digital pathology, expansion is accelerating across the Middle East, Asia, and South America.

The goal is simple but ambitious:
Connect institutions worldwide so they can share expertise, consult with each other seamlessly, and collaborate on research—regardless of geography or resource availability.

This federated network enables:

  • Easier consultations across continents
  • Shared AI testing and deployment
  • Large-scale validation studies
  • Equitable access to specialized expertise
  • Cross-border clinical trial support

As digital pathology infrastructures mature, the global federated model will become increasingly central to innovation, patient care, and scientific discovery.

A Call to Action: Join the Pathoverse

Dr. Singh closed with an inspiring metaphor: everyone working to advance pathology is a “superhero,” each bringing unique strengths, insights, and innovations. But the real power comes when these efforts converge.

The Pathoverse aims to unite those superheroes into a connected ecosystem—one where silos disappear, data flows freely, and the world of pathology acts as a single, collaborative community.

The message was clear: There is no other way to succeed except by working together.

Whether through shared research infrastructure, AI partnerships, cloud-enabled workflows, or international collaboration, the future of pathology depends on collective action.

Dr. Singh invited everyone, from pathologists, researchers, technologists, AI companies, to healthcare leaders, to join the movement. The Pathoverse is open, growing, and ready to accelerate the global evolution of digital pathology.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.

Pathoverse Part 5: Accelerating Clinical Trial Enrollment

This article summarizes part 5 of our “Into the Pathoverse” webinar, recorded at Pathology Visions 2025 in San Diego and available on-demand. This segment starts at 37:02 in the full video. Watch the full video.

In the fifth segment of the Pathoverse webinar, Travis Wold, CEO of Imagenomix, shared a candid and energetic look at how his team is tackling one of oncology’s most stubborn challenges: clinical trial enrollment. With humor, personal anecdotes, and a clear mission rooted in his upbringing in Alaska, Wold explained how Imagenomix Predict is reshaping patient identification and trial matching—particularly for rare mutations that traditional workflows struggle to detect efficiently.

Imagenomix, a spinoff from NYU, was founded with a bold purpose: democratize precision diagnostics around the world. For Wold, this mission is personal. Growing up in a region with limited access to specialized healthcare, he understands firsthand the gaps that leave patients without the testing or treatment options widely available elsewhere. Today, his company is building the tools to bridge those gaps, beginning with clinical trials.

The Clinical Trial Enrollment Problem

Wold opened by highlighting a painful statistic: 40% of oncology clinical trials fail due to under-enrollment. The barriers are well known across the industry:

  • NGS testing is slow and expensive
  • Many patients never receive sequencing at all
  • Delays in molecular testing mean delays in screening, enrolling, and ultimately treating patients
  • Slow enrollment directly impacts regulatory timelines and revenue for pharma companies
  • Academic centers often want to support trials but lack efficient tools to identify eligible patients quickly

The result is a mismatch between clinical trial goals and real-world diagnostic workflows. “It’s not that people don’t want to participate,” Wold emphasized. “It’s that we’re starting the identification process too late.”

Enhancing—Not Replacing—NGS

One misconception Wold frequently encounters is the idea that Imagenomix is trying to replace next-generation sequencing. “We’re not,” he clarified. “We’re making it more efficient.”

The company’s platform, Imagenomix Predict, uses slide-based analysis to rapidly screen for specific mutations—identifying likely positives before a patient ever undergoes sequencing. Consider lung cancer: only about 25% of U.S. lung cancers are molecularly tested. Globally, the number drops to 2% or less due to cost and access constraints.

With breast cancer, Wold illustrated a real challenge: AKT mutations occur in only about 5% of cases. If only a quarter of patients receive sequencing, the subset with rare actionable mutations becomes even harder to find. Many trials struggle to identify eligible patients within reasonable timelines.

Imagenomix flips that model. Instead of enrolling patients first, paying for sequencing, and discovering months later that they do not qualify, Imagenomix Predict screens slide images upfront for markers associated with the mutation. “We proved the biology before the trial even began,” Wold said. “Now we’re helping centers find these patients instead of hoping they appear.”

Speeding the Diagnostic Pathway

Wold contrasted the traditional timeline of NGS workflows with Imagenomix’s accelerated approach. At NYU, internal data showed that from biopsy to final NGS result, the process takes 33 to 42 days on average—even within a unified health system.

Imagenomix Predict compresses early steps dramatically:

  1. Day 0–1: Slides are scanned, often using a Grundium unit paired with PathPresenter.
  2. Within 30 minutes: Imagenomix Predict generates an initial probability report for the target mutation.
  3. Confirmation testing follows (PCR, ddPCR, or small panel NGS), maintaining clinical standards while reducing wasted sequencing.

This hybrid model—AI-driven triage plus gold-standard confirmation—enriches trial cohorts and accelerates time to enrollment.

Scaling Across 45 Clinical Trial Centers

As Imagenomix prepared to expand into 45 clinical trial sites with its first pharma partner, the team faced a challenge: each center had different scanners, LIS systems, and IT approvals. Some institutions did not allow software downloads; others required lengthy validation processes. The pharma sponsor also needed consistent reporting across all sites.

This is where PathPresenter became essential.

Wold explained that PathPresenter already had a footprint across many of the target institutions. Its vendor-agnostic design and no-download deployment model offered an immediate advantage. “Simplicity was everything,” he said. “PathPresenter made the whole system plug-and-play across dozens of sites.”

Combined with AWS—whose cloud services support the underlying compute and data exchange—Imagenomix was able to roll out Imagenomix Predict to 45 centers faster than expected. Wold thanked AWS for its grant support and sponsorship in helping launch the initiative.

Real-World Results: Early Mutations Identified

Despite being only a month into the first trial deployment, Imagenomix has already seen meaningful results. Wold shared that the platform has successfully identified AKT mutations early, enabling rapid confirmatory testing and immediate enrollment.

The output report, which includes probability scoring and supporting features, serves as a triage tool rather than a replacement for confirmatory assays. “Do no harm,” Wold emphasized. “We are not here to bypass gold-standard methods. We’re here to make sure those tests are being used efficiently—and on the right patients.”

Looking Ahead: Beyond Mutation Detection

While Imagenomix currently focuses on lung and breast cancer, Wold revealed that the company is developing a proprietary pipeline targeting recurrence rather than mutation status. These new products are expected to launch publicly next year and could expand Imagenomix’s reach far beyond trial enrichment.

Their long-term mission remains unchanged: make precision diagnostics accessible globally, not just in large, well-resourced academic centers.

A Glimpse of Digital Pathology’s Collaborative Future

Wold closed by sharing his excitement about the digital pathology ecosystem represented at the event. The field is full of specialized companies, each solving different parts of the puzzle. The next five years, he predicted, will bring dramatic collaboration and consolidation as these companies begin working together across workflows, tools, and data infrastructures.

In many ways, Imagenomix Predict—and its integration with PathPresenter and AWS—is an early example of that future: a connected, interoperable ecosystem designed to accelerate diagnosis, improve trial enrollment, and ultimately deliver better options to patients who need them.

Wold encouraged attendees to reach out during the event and continue the conversation about what digital pathology, AI, and cloud infrastructure can achieve when brought together under one vision.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.

Pathoverse Part 4: Cloud Infrastructure for Scalable Digital Pathology

This article summarizes part 4 of our “Into the Pathoverse” webinar, recorded at Pathology Visions 2025 in San Diego and available on-demand. This segment starts at 27:00 in the full video. Watch the full video.

In the fourth segment of the Pathoverse webinar, Sasha Paegle from Amazon Web Services (AWS) offered a clear and insightful look at how cloud technologies are reshaping the digital pathology landscape. While most people recognize the Amazon brand, Sasha began by highlighting a point that often surprises audiences: Amazon has been deeply invested in healthcare and life sciences for more than 18 years. AWS, the cloud-computing arm of Amazon, now has one of the world’s most experienced teams in healthcare-focused information technology.

Sasha himself is an example of that blend of scientific and technical expertise. Trained originally as a molecular biologist, he moved into the worlds of omics, high-performance computing, and large-scale data analytics—eventually joining the AWS Healthcare & Life Sciences team. His background mirrors a broader trend within AWS: individuals who combine decades of IT experience with a deep understanding of biomedical research, clinical workflows, and patient-centric innovation.

AWS in Healthcare: A Long History of Modernization

Over nearly two decades, AWS has worked with healthcare organizations to modernize their IT infrastructure with a consistent vision: use cloud-based technologies to improve patient outcomes. While AWS is often associated with storage or computing power, Sasha explained that the platform has grown far beyond those capabilities. Today it includes a suite of industry-specific services designed explicitly for healthcare. These include:

  • Amazon HealthLake, which unifies structured and unstructured data across modalities for analytics, search, and machine learning
  • Amazon Comprehend Medical, a natural language processing service tailored to clinical text
  • Transcribe Medical, for speech-to-text clinical documentation
  • Amazon HealthOmics, purpose-built for storing and computing on omics data, from FASTQ files to BAMs
  • Amazon HealthImaging, a newer service now poised to play a major role in digital pathology

This expanding ecosystem reflects AWS’s broader goal: reduce the technical burden on healthcare organizations so they can focus on value, insights, and clinical impact.

Global Scale and Reliability for Medical Imaging

Sasha then shifted to AWS’s global footprint, a critical foundation for enabling the Pathoverse. AWS currently operates across 38 global regions, allowing healthcare organizations to take advantage of cloud compute resources closer to where the data originates. This reduces latency, improves accessibility, and enables fast, secure exchange of medical images—whether across hospital systems or across continents.

Durability and reliability are also central design principles of AWS infrastructure. The systems behind services like S3 and HealthImaging are engineered to minimize downtime and withstand demanding clinical workloads. Their stability has earned AWS broad recognition across industry analysts. Sasha noted that AWS was recently named the #1 cloud provider by KLAS, its first year being evaluated in that category. IDC and Gartner have reached similar conclusions.

What “Managed Services” Mean in Healthcare

To help the audience understand AWS’s approach, Sasha introduced the idea of managed services, a concept that can sometimes feel abstract. He explained it using a simple metaphor: imagine AWS’s core technologies—compute, networking, storage—as a massive collection of Lego bricks. Expert users can assemble those bricks into almost anything, but it takes time and specialized knowledge.

Managed services are essentially pre-built structures made from those bricks. AWS engineers take the foundational components and assemble them into ready-to-use solutions that remove undifferentiated heavy lifting. This allows partners like PathPresenter to focus entirely on building high-value applications rather than spending weeks or months configuring basic infrastructure.

AWS HealthImaging: Built for Speed, Scale, and Interoperability

Sasha described HealthImaging as one of the most important of these managed services, particularly in the context of the Pathoverse vision. HealthImaging is purpose-built to store, manage, and serve medical images at scale—supporting fast retrieval, high performance, and cost efficiency. Its design principles include:

  • Store once, use many times: images remain available for multiple workflows without duplication
  • Lower cost of development, with AWS estimating up to 40% time and cost savings compared to building imaging pipelines from scratch
  • Instantaneous image access, ensuring clinicians experience virtually no lag
  • Built-in lifecycle policies, automatically moving images between storage tiers based on usage patterns
  • Industry-specific APIs, including full DICOM API support
  • HIPAA eligibility, enabling secure exchange of protected health information

Sasha noted that when he joined AWS five years ago, many organizations insisted that medical images—especially high-resolution ones—could never be processed efficiently in the cloud. Since then, AWS has repeatedly proven that assumption wrong, first by optimizing object storage for low-cost, high-speed access, and later by launching HealthImaging to support high-performance, multimodal imaging workflows.

From Radiology to Pathology: The Evolution Ahead

While HealthImaging originally centered on radiology, Sasha confirmed that the service is now evolving toward full support for pathology images, including whole-slide imaging from any scanner platform. This expansion directly aligns with the goals of the Pathoverse: enabling organizations to store digital slides once and reuse them many times—for diagnosis, consultation, education, AI development, research, and more.

Over time, AWS aims to make HealthImaging a universal imaging backbone capable of supporting Radiology, Pathology, Cardiology, Ophthalmology, and other imaging-heavy specialties. This multi-modality future will make it possible for platforms like PathPresenter to orchestrate workflows seamlessly across data types and clinical domains.

Enabling the Pathoverse Vision

Sasha concluded by tying AWS’s capabilities back to the broader goals of the Pathoverse: removing friction, enabling interoperability, and supporting diverse use cases—from remote consults to AI-driven insights to global data exchange.

The cloud, he explained, thrives at the intersection of scalability and collaboration. As AWS continues developing services like HealthImaging, HealthLake, and HealthOmics, the foundation for universal digital pathology becomes stronger—and the vision of a connected Pathoverse becomes increasingly achievable.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.

Pathoverse Part 3: Lowering Barriers and Driving Consult Efficiency

This article summarizes part 3 of our “Into the Pathoverse” webinar, recorded at Pathology Visions 2025 in San Diego and available on-demand. This segment starts at 16:23 in the full video. Watch the full video.

Digital pathology may feel like a futuristic vision, but in many ways the future is already here. What’s missing is widespread adoption. As Todd Vanden Branden, Senior Director of Marketing and Field Applications for Grundium, explained in this segment of our “Into the Pathoverse” webinar, the first obstacle to digital pathology isn’t complex AI or advanced analytics—it’s often something far more fundamental: the scan. Until a lab can afford to reliably digitize slides, the rest of the digital ecosystem simply can’t take shape.

And yet, many labs still struggle to take that first step.

The Pressure Cooker Facing Pathology

Anyone working in pathology is all too familiar with the pressures Todd described. Case volumes continue to rise, while the pipeline of new pathologists shrinks. In a recent presentation, Dr. Parwani from Ohio State noted that more than 700 pathology positions are currently open in the U.S.—and that number isn’t improving. Subspecialty gaps in fields like cytopathology, hematopathology, GI, dermpath, and neuropathology widen each year.

At the same time, slides don’t always sit where the expertise resides. A specimen may be hundreds of miles away from the subspecialist best equipped to interpret it. Combined, these issues create what Todd called a “perfect storm.”

Digital pathology and AI have the potential to ease that storm—but only after labs begin scanning. Today, depending on who you ask, only 15–30% of U.S. labs have adopted digital workflows. The majority haven’t even started.

So why is that?

What’s Holding Labs Back

Todd outlined four major barriers:

1. Financial constraints.
Traditional scanners come with big price tags, ongoing subscription fees, licensing costs, and consumables. For many labs—especially smaller ones—the return on investment feels too distant.

2. Space limitations.
Few labs have extra room to spare, and slide scanners are often known for their bulky footprints.

3. IT complexity.
Integration with LIS and EMR systems, plus growing cybersecurity requirements, can intimidate even well-resourced IT teams.

4. Workflow disruption.
Pathology isn’t a field that embraces change lightly. New tools can introduce learning curves, slowing day-to-day operations before they improve them.

These challenges create hesitation—not because labs don’t value digital pathology, but because adopting it feels overwhelming.

What Labs Need for Digital Adoption

Todd made an important point: to accelerate digital adoption, scanners themselves must evolve to meet the real needs of labs. Here’s what he argues scanners must offer:

  • Reasonable capital costs with no hidden subscription or licensing fees, enabling faster ROI.
  • A small footprint—ideally compact enough to sit where a slide folder already does.
  • Simple, secure IT integration that aligns with modern cybersecurity standards.
  • Easy, intuitive workflows that minimize training time and resistance to change.

Fortunately, solutions that meet these criteria already exist.

How Grundium Scanners Break Down Barriers

Grundium is one of the scanner providers redefining accessibility in digital pathology. Todd highlighted several ways their Ocus family of scanners fits the needs of modern labs:

  • High-quality imaging with both single-slide and four-slide models (at 20x or 40x magnification).
  • A small, portable footprint, allowing scanners to sit directly on a bench without reconfiguring the lab.
  • A web-based, intuitive user interface, reducing workflow friction.
  • No subscriptions, licensing fees, or consumable costs.
  • Strong connectivity, enabling quick image transfer and secure remote collaboration.
  • Smooth IT deployment, made to operate comfortably within existing infrastructure.

Because of this, Grundium scanners aren’t just for labs stepping into digital pathology for the first time. They’re equally useful for digitally mature centers seeking flexible point-of-care or remote-consult capabilities. Todd likes to think of them as “and” technology rather than “or” technology—a complement to larger enterprise systems, not a replacement.

A Real-World Example: OSU Wexner Cancer Center

One compelling case study comes from the Ohio State University Wexner Cancer Center, a recognized leader in digital pathology. As part of its Community Pathology Program, OSU uses Grundium’s Ocus M40 scanner alongside PathPresenter to streamline consult workflows across partner hospitals.

Traditionally, obtaining a second opinion for complex cases can be slow and risky. Physical slides must be transported, which introduces delays, fragmentation, and potential for loss or damage—none of which serve the patient who urgently needs a diagnosis. With the Ocus M40 and PathPresenter, the workflow becomes almost seamless:

  1. A slide is scanned locally.
  2. The image is sent directly through the scanner interface to PathPresenter.
  3. A remote subspecialist reviews it and assists in diagnosis.

At Worcester Community Hospital, a partner site, this digital consult workflow improved turnaround time by 97.8%. What once took an average of 23 hours now takes about 30 minutes. That kind of impact isn’t just operational, it’s clinical.

Never Forget What’s at the Center: The Patient and the Pathologist

Todd closed his segment with two reflections from practicing pathologists that underline why this work matters.

Dr. Parwani emphasized that when digital consult workflows are implemented well, they don’t just speed up diagnoses—they strengthen ROI for departments.

Dr. Schumacher from Worcester Community Hospital added a deeply human perspective: digital pathology elevates diagnostic quality, supports continuous learning, and makes the work itself more engaging. As she put it, it “makes the job a lot more fun and interesting.”

And that’s an important reminder. Yes, digital pathology involves impressive technology and groundbreaking AI. But at the end of the day, it’s about two things: improving patient care and supporting the people who deliver it.

The First Step Is Often the Most Important

Digital pathology has the power to expand access to specialists, strengthen smaller hospitals, and connect clinicians across geographies. But before any of that can happen, labs must take the first step—adopting scanning. By lowering barriers related to cost, space, IT, and workflow, scanners like the Grundium Ocus series make that step not just possible, but practical.

As the Pathoverse continues to grow, this foundational shift toward accessible scanning will be one of the key drivers of digital transformation—and ultimately, better care for patients everywhere.

More Information

Interested in learning more about how these solutions can help solve your own challenges? Contact us.